Mechanics, anisotropy, electrical propagation, mass transport, vascularization, immune response, and the coupled constraints behind engineered cardiac tissue.
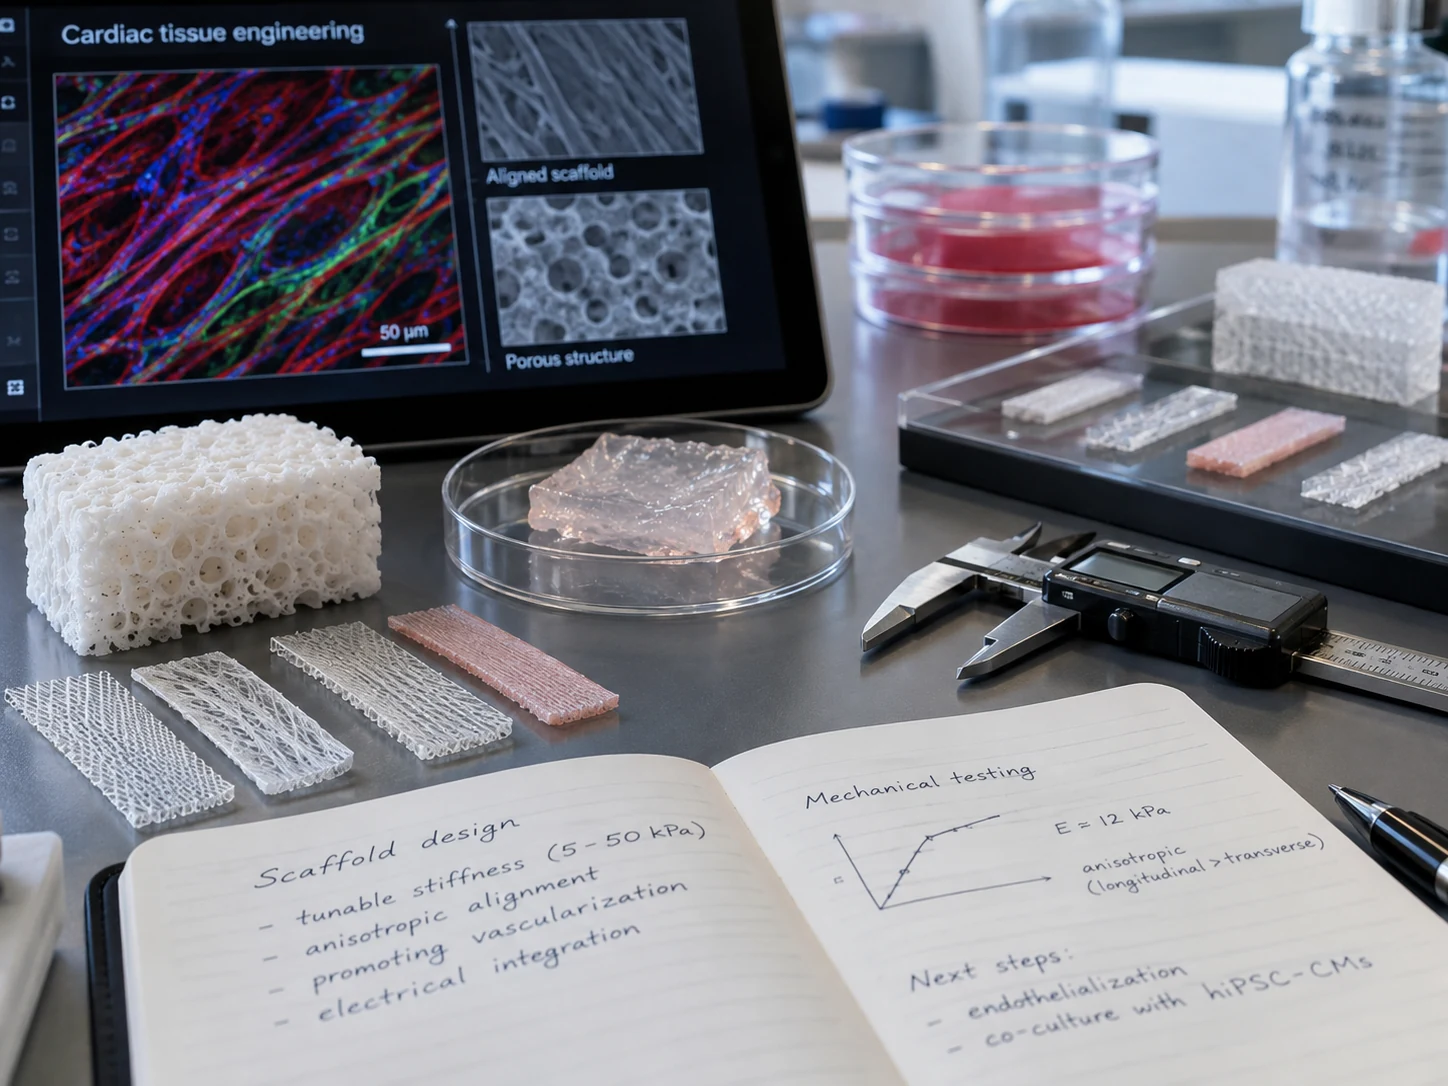
The post-infarct ventricle is anisotropic, mechanically heterogeneous, electrically active, vascularly constrained, and immunologically dynamic. A graft or scaffold therefore cannot be optimized on stiffness alone. Its useful design space is defined by several interacting constraints that can improve one axis while worsening another.
| Axis | Why it matters | What is measured | Common failure mode |
|---|---|---|---|
| Stiffness / viscoelasticity | Controls force transfer, mechanosensing, and ventricular restraint. | Elastic modulus, stress relaxation, fatigue, strain response. | Mismatch creates stress concentration or pathological remodeling. |
| Anisotropy / architecture | Cardiac fibers align force and conduction directionally. | Fiber orientation, pore geometry, alignment metrics. | Isotropic tissue fails to reproduce native mechanics or propagation. |
| Electrical integration | New tissue must activate with surrounding myocardium. | Conduction velocity, action-potential propagation, junctional coupling. | Slow or heterogeneous conduction creates arrhythmogenic substrate. |
| Mass transport / vascularization | Thick constructs rapidly become diffusion-limited without perfusion. | Oxygen consumption, diffusion, vessel density, perfusion. | Central necrosis and loss of graft function. |
| Immune / inflammatory response | Material chemistry and degradation products shape host response. | Macrophage state, cytokines, fibrosis, foreign-body response. | Chronic inflammation, encapsulation, or excess scar. |
| Degradation / remodeling | Support should evolve as host tissue changes. | Mass loss, mechanical retention, degradation products. | Loss too early or persistence that blocks remodeling. |
Offers direct mechanical support and a controlled construct geometry. Surgical delivery and host integration are major constraints.
Can fill injured regions with less invasive delivery and carry cells or factors. Shape control, retention, and spatially uniform integration are harder.
Attempts true remuscularization with pre-organized cells and matrix. Vascularization, maturation, scale, and electrophysiologic integration are demanding.
Uses mechanics, chemistry, degradation, or factor release to steer endogenous repair. It avoids cell-manufacturing complexity but depends on host regenerative capacity.
At concept stage, the computational role is to eliminate obviously incompatible regions of the design space before expensive fabrication. That includes finite-element estimates of stress redistribution, simple diffusion / transport models, sensitivity analysis around material properties, and explicit risk gates for electrical mismatch, vascular insufficiency, and inflammatory persistence.
